

Hello Avatar! Welcome to another week of biotech analysis. Today’s commentary, as always on Thursday, focuses on the general market update. This week confirmed the playbook. Biotech can rally and capital can return quickly, but funding is flowing to companies with clean catalysts and tight execution. Secondaries continue to dominate the financing landscape, while IPO activity remains scarce. Investors are rewarding near-term proof and punishing duration risk. In this environment, cost of capital shapes trial design, and clock discipline matters as much as mechanism.
We are now publishing 7x per week according to the following cadence:
Mondays: Stocks
Tuesdays: Biotech
Wednesdays: Podcast
Thursdays: Markets
Fridays: News
Saturdays: Podcast
Sundays: Strategy
We are also publishing unique content on X - be sure to follow up if you are not already @BowTiedBiotech. And to check-out the archive of our work on X you can find it on our website at: BowtiedBiotech.subtack.com/x-articles.
SUBSCRIBE TO PODCAST HERE:
Please help spread the work by subscribing and hitting the share button if you are enjoying content!
Lots to cover this week, let's get started!

Macro Update
The macro tape is getting harder to ignore for biotech. The headline market still looks risk-on because AI, semis and mega-cap tech are absorbing capital, but the plumbing underneath is less clean. Reuters reported that equity financing costs recently spiked to roughly 200 bps above the fed funds rate, the highest level since December 2024, while dealer equity exposure reached about $211B in late June. That is not a normal “broad risk appetite is back” setup. It is a concentrated, levered trade clustered around the market’s favorite sectors.
That matters for biotech because the sector is still duration-heavy, cash-hungry and dependent on open capital markets. The Fed held rates at 3.50%-3.75% in June while saying inflation remains elevated relative to its 2% target, and the 10-year and 30-year Treasury yields remain high enough to keep pressure on long-duration equities. For a profitable mega-cap software company, that is an annoyance. For a Phase 1 oncology platform with 12 months of cash, it is the entire story.

The biotech IPO window is technically open, but that is not the same thing as a real sector reopening. BioPharma Dive counted 13 venture-backed biotech IPOs so far in 2026, with 11 raising at least $250M, which sounds constructive on the surface. The catch is that this is a selective window for large, clean, institutionally pre-sold stories, not a return to 2021-style indiscriminate funding. The market will fund obesity, late-stage derisked assets and credible crossover-backed names. It is still much less forgiving toward small-cap platforms, thin cash runways and “transformational” early data packages.
The bear read-through is straightforward. If the AI trade keeps working, biotech may remain starved for attention because capital has a better, more liquid momentum home. If the AI trade cracks, biotech probably does not become the safe haven. It becomes a source of liquidity. In this tape, the right biotech screen is not “what has the biggest upside if the data work.” It is balance sheet first, catalyst quality second, financing path third. Anything that needs the market to stay generous deserves a discount.
Introduction
This week we’re stepping away from the usual biotech catalyst tape and looking at the macro variable the sector keeps pretending it can outrun. Energy shocks, sticky long rates, and inflation pressure do not just move the 10 year. They decide which therapeutic stories get funded, which trials survive, and which companies run out of time before the biology gets a fair hearing. The easy read is that this is a market structure problem. The better read is that macro pressure is starting to reshape therapeutic development itself. If time is expensive, then translation has to get faster. If volatility is persistent, then resilience becomes druggable.
Why this matters this week
Biotech investors keep looking for the sector catalyst. Rate cuts. IPO reopenings. M&A. Better FDA tone. Pick your favorite. The cleaner read is less comforting. Biotech is still a duration trade sitting inside a macro tape that keeps punishing duration whenever inflation risk returns. Energy shocks make that worse because they hit the market in two places at once. They raise input costs and keep long rates sticky. That matters for every therapeutic company asking investors to value cash flows that sit five to ten years away.
The current setup is not theoretical. The Fed held rates at 3.50 percent to 3.75 percent in June and said inflation remains elevated relative to its 2 percent target, in part because supply shocks have pushed prices higher in sectors including energy. That is the entire biotech problem in one sentence. A drug developer can run a clean Phase 2, show a real biomarker move, and still get valued like the market does not care because the discount rate moved against it. The science improved. The equity got worse. Both can be true.
This is where the overlooked therapeutic angle starts. Energy shocks do not just change oil prices. They change what kind of biotech deserves capital. They favor assets that prove value fast, generate clinical signal in cheap populations, avoid bloated manufacturing footprints, and sell into medical systems where reimbursement does not rely on a perfect consumer economy. They punish assets that need long trials, large primary care sales forces, heavy CMC spend, imported reagents, and three follow on financings before anyone knows if the drug works.
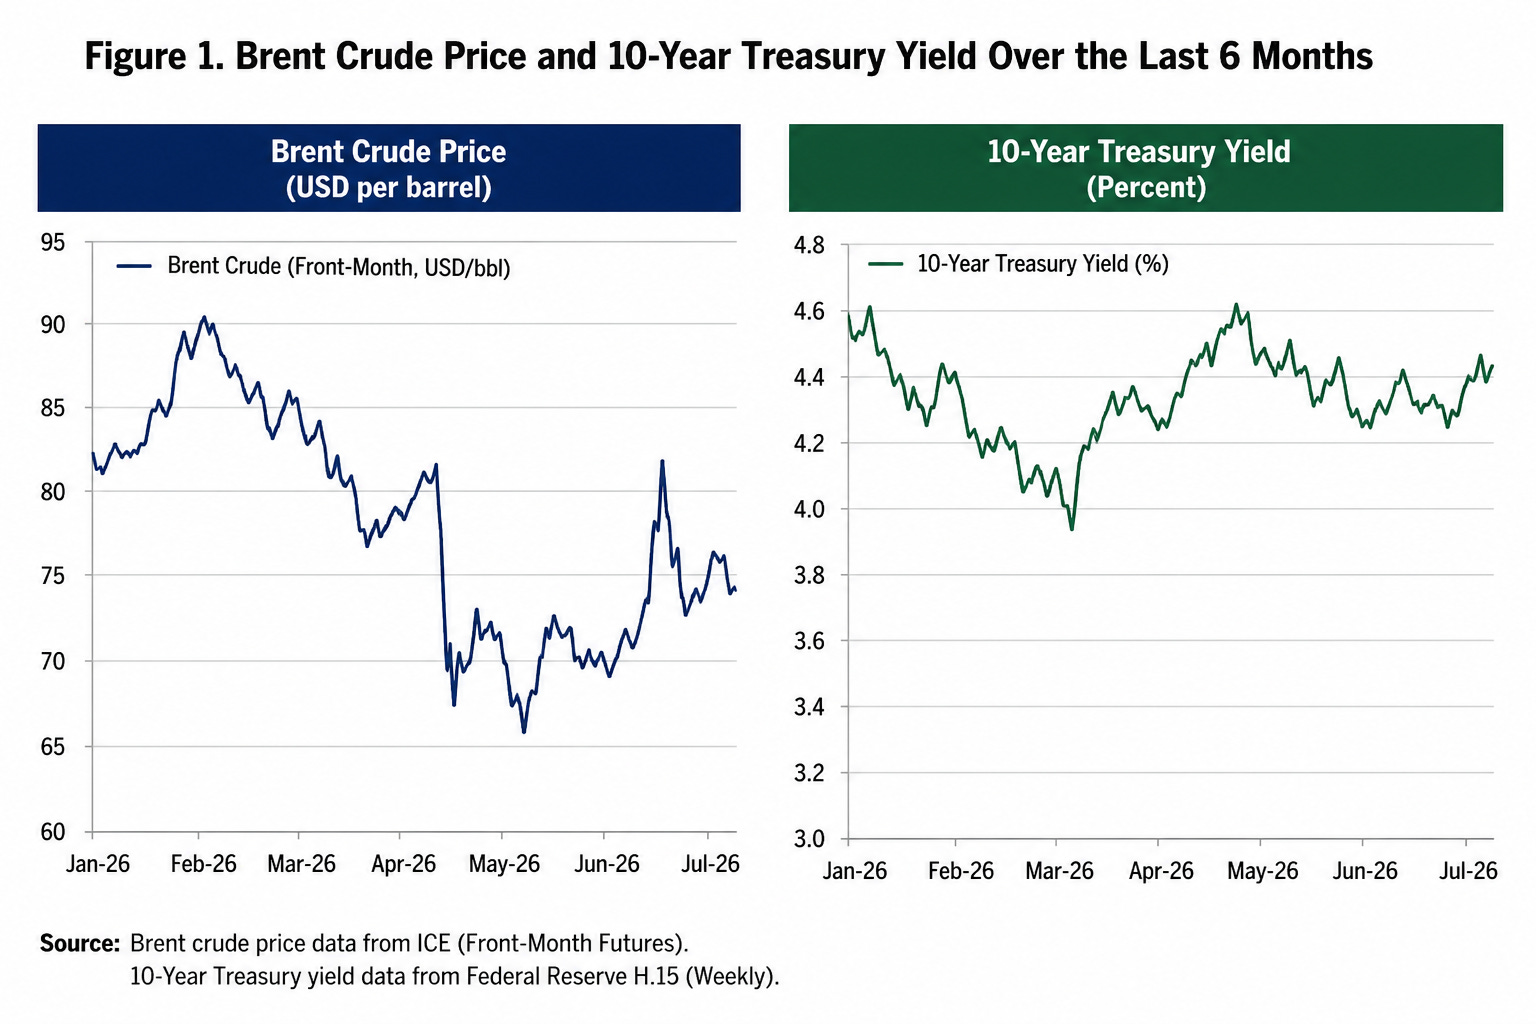
The market is telling you the sector has less time
The lazy bullish version says oil dipped, tech rallied, and risk appetite is fine. Reuters reported that Brent settled near $76.30 on July 9 after falling roughly 2 percent even as Middle East tension disrupted flows and delayed reopening through the Strait of Hormuz. The market did not panic. That is true. It is also incomplete. The more important detail is that Fed officials remain focused on inflation risk from energy, while the 10 year Treasury sat around 4.55 percent. Biotech does not need a full oil shock to feel pain. It just needs enough energy volatility to keep the Fed from rescuing duration.
You should care because most biotech models quietly assume time is cheap. Time to enroll. Time to dose. Time to manufacture. Time to raise money after the next data cut. Time to wait for payer clarity. That assumption worked when money had no yield. It does not work when cash earns real return and investors can buy quality elsewhere. Every extra quarter of trial duration now competes against Treasury yield, AI liquidity, and pharma licensing alternatives.
This changes how you should read therapeutic development. The best programs are no longer just the ones with the biggest biology. They are the ones with the shortest path to a hard decision. A smaller trial with a high quality biomarker and a clean go or no go can beat a sexier platform that needs 700 patients and three years to tell you something ambiguous. In this tape, ambiguity is expensive. Delay is toxic.
Energy shocks translate into biology before they translate into biotech
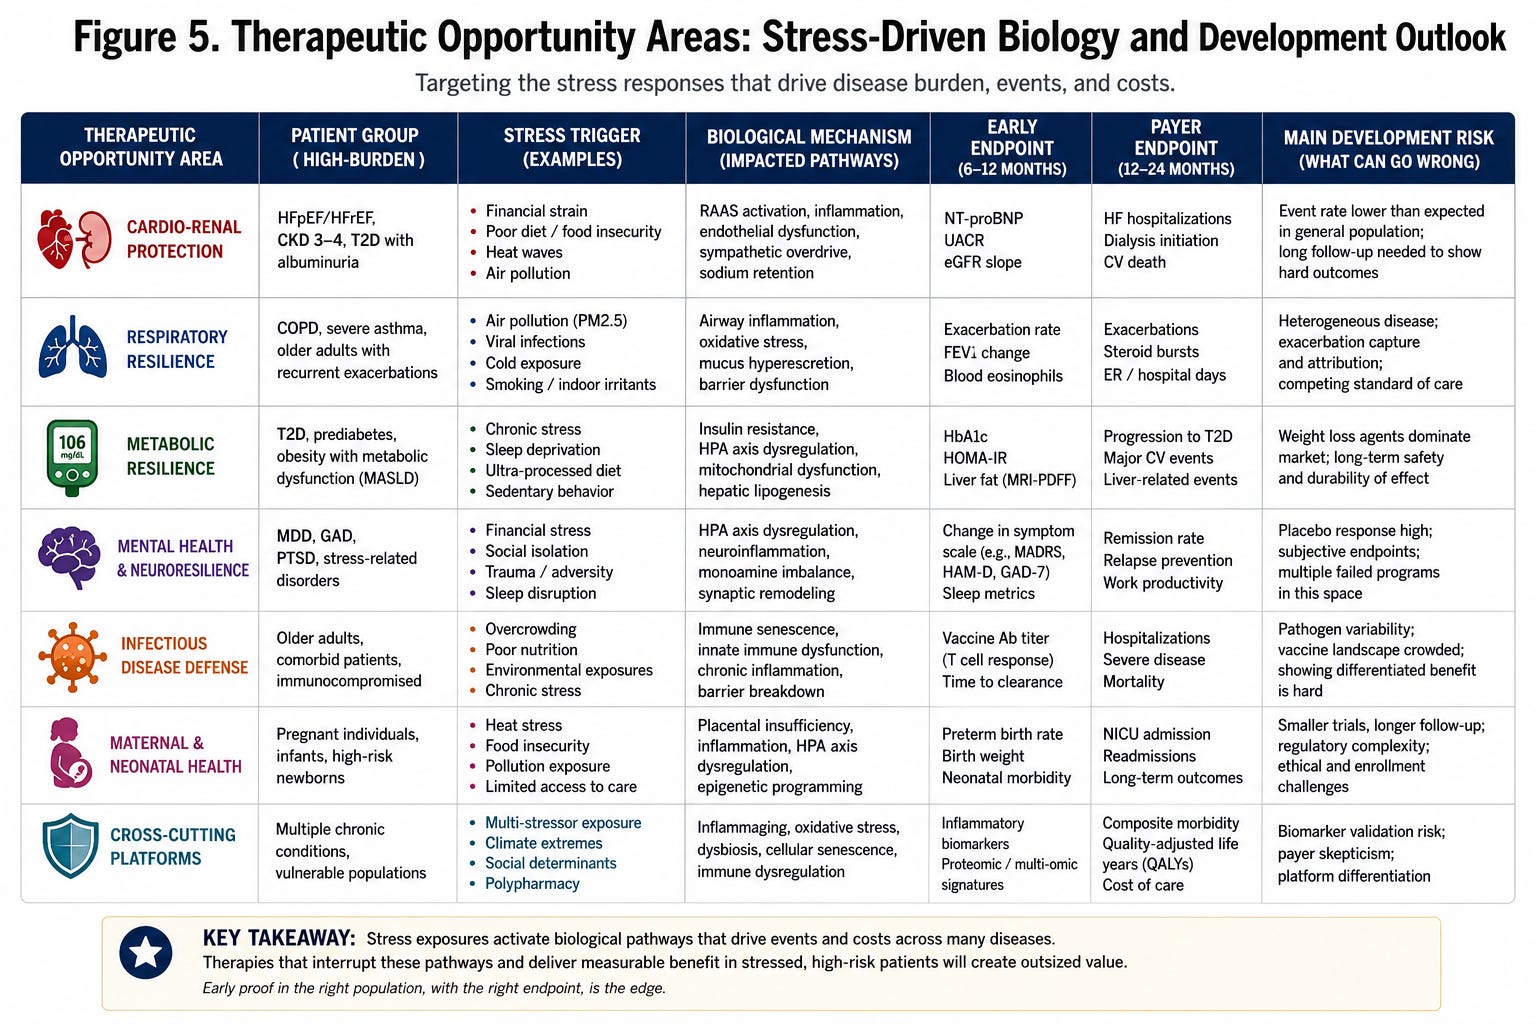
The obvious market read is that energy shocks hurt biotech multiples. The more interesting read is that energy stress also creates disease pressure. Heat, pollution, power interruptions, food cost inflation, medication nonadherence, and strained health systems all push patients into worse outcomes. That is not a neat therapeutic category. It is a stress test across cardio renal disease, respiratory disease, metabolic disease, pregnancy, infectious disease, and frailty.
That matters because biotech tends to build programs around stable disease definitions. Real patients do not live inside stable disease definitions. A COPD patient exposed to wildfire smoke and high energy costs becomes a different patient. A heart failure patient who cuts back on cooling during a heat wave becomes a different patient. A diabetic patient who delays refills because household expenses rose becomes a different patient. The biology did not change in a textbook way. The environment changed the phenotype.
This is where investors miss something. Energy volatility creates a market for therapies that protect patients during stress, not just therapies that improve baseline disease. The drug that prevents decompensation during heat, pollution, infection, or medication disruption has a different value proposition than the drug that moves an average endpoint in a controlled trial. The development challenge is proving it. The commercial opportunity is that stressed systems pay for avoided hospitalizations when the signal is real.
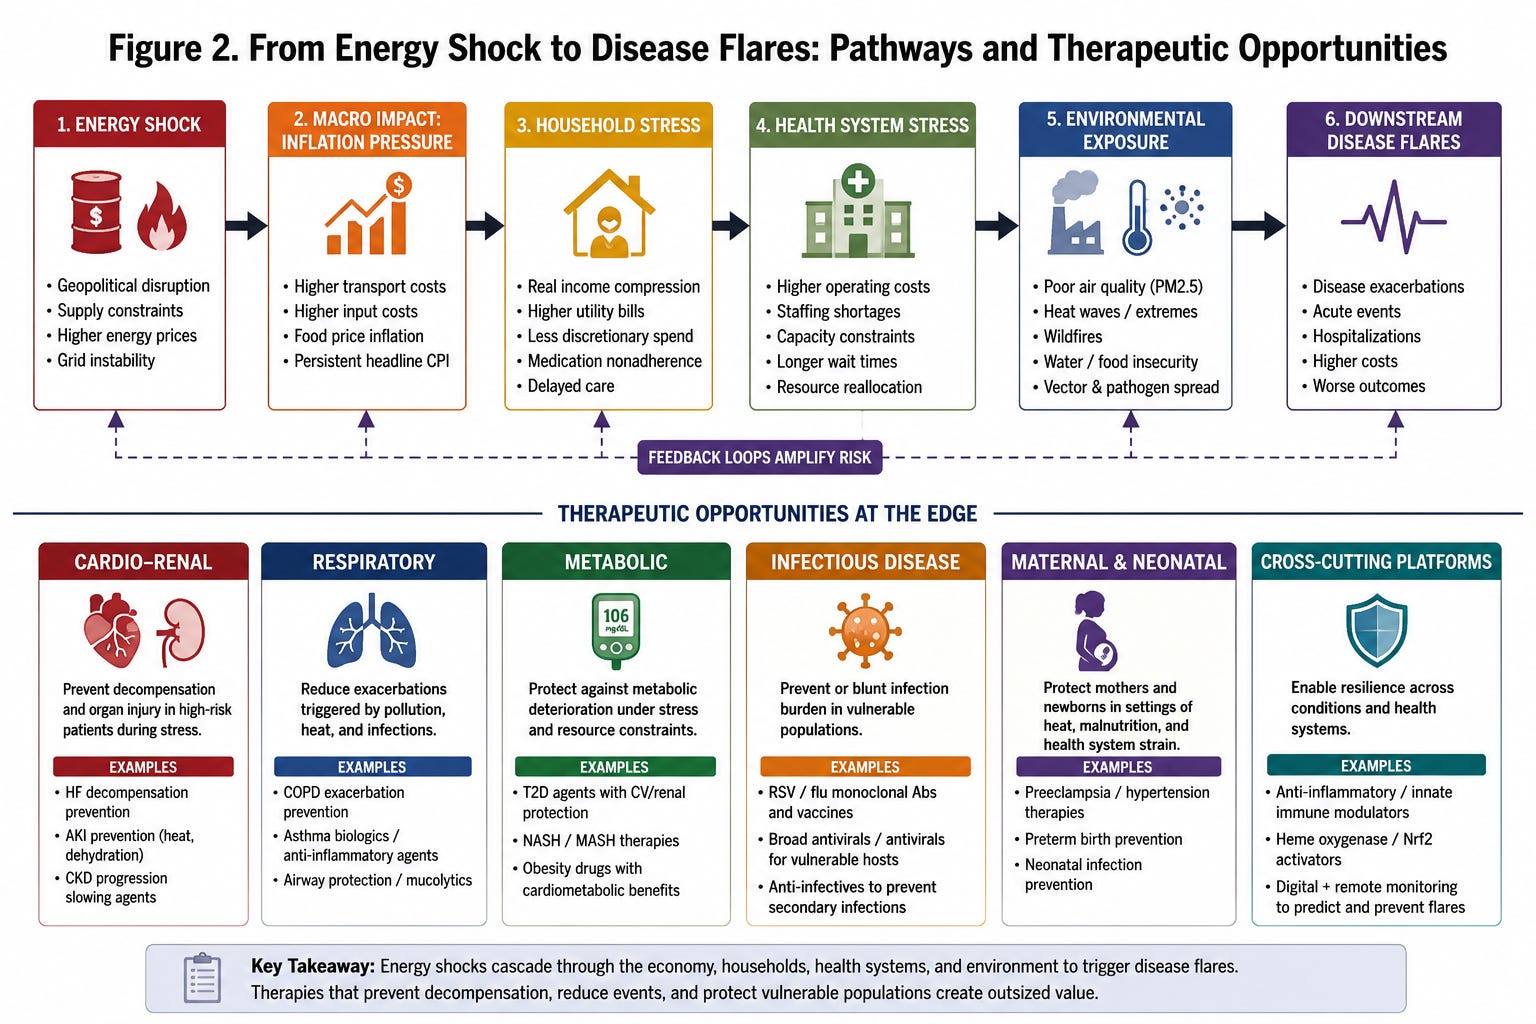
The overlooked field is resilience medicine
The phrase sounds soft. The biology is not. Resilience medicine means treating the patient’s capacity to survive external stress without tipping into hospitalization, organ injury, or functional decline. Biotech already does this in fragments. SGLT2 inhibitors reduce heart failure events. RSV antibodies protect infants through a seasonal exposure window. Anti inflammatory drugs target flare biology. Antivirals compress risk during infection. The missing piece is that energy and climate volatility turn these fragments into a larger development theme.
This field will reward drugs that show event reduction under stress. That includes acute kidney injury prevention during heat exposure, reduction of COPD exacerbations during pollution spikes, protection from heart failure decompensation during extreme temperatures, and faster recovery from viral or bacterial insults in frail patients. These are not lifestyle wellness ideas. They are hospital avoidance products. That is what makes them investable.
The hard part is trial design. You cannot build a company on a vague claim that the world is getting hotter or oil is volatile. You need a population with predictable stress exposure, a measurable biological response, and an endpoint payers care about. That pushes development toward pragmatic trials, claims linked designs, seasonal enrichment, wearable assisted monitoring, and geographically targeted enrollment. The winners will not just have good molecules. They will know when and where to test them.
Long rates force better therapeutic taste
High long rates are a brutal filter. They make investors ask whether a program earns the right to exist before Phase 3. That sounds obvious. Most biotech portfolios still fail the test. They carry too many indications, too many exploratory cohorts, and too much platform language. You can get away with that in a zero rate market because optionality has a bid. In this market, optionality gets treated like spending.
The therapeutic implication is simple. Development teams need assets with early human translation that changes capital access. That means target engagement in tissue, a biomarker tied to clinical outcome, a patient group with high event rates, and a financing event that does not require investors to believe six things at once. If your Phase 1 only proves tolerability in healthy volunteers, the market will not pay much. It has seen that movie. If your Phase 1b shows target engagement in sick patients with a credible directional clinical effect, you have something.
This is one reason obesity, rare disease, immunology, and later stage endocrine assets continue to attract capital while broad speculative platforms struggle. They offer cleaner narratives around patient selection, commercial demand, and pharma fit. Vertex buying Crinetics for around $10 billion fits that pattern. The buyer did not pay for a loose platform dream. It paid for an approved acromegaly drug, a late stage CAH asset, and a potential endocrine franchise. That is what duration compression does. It turns buyers into accountants with scientific taste.
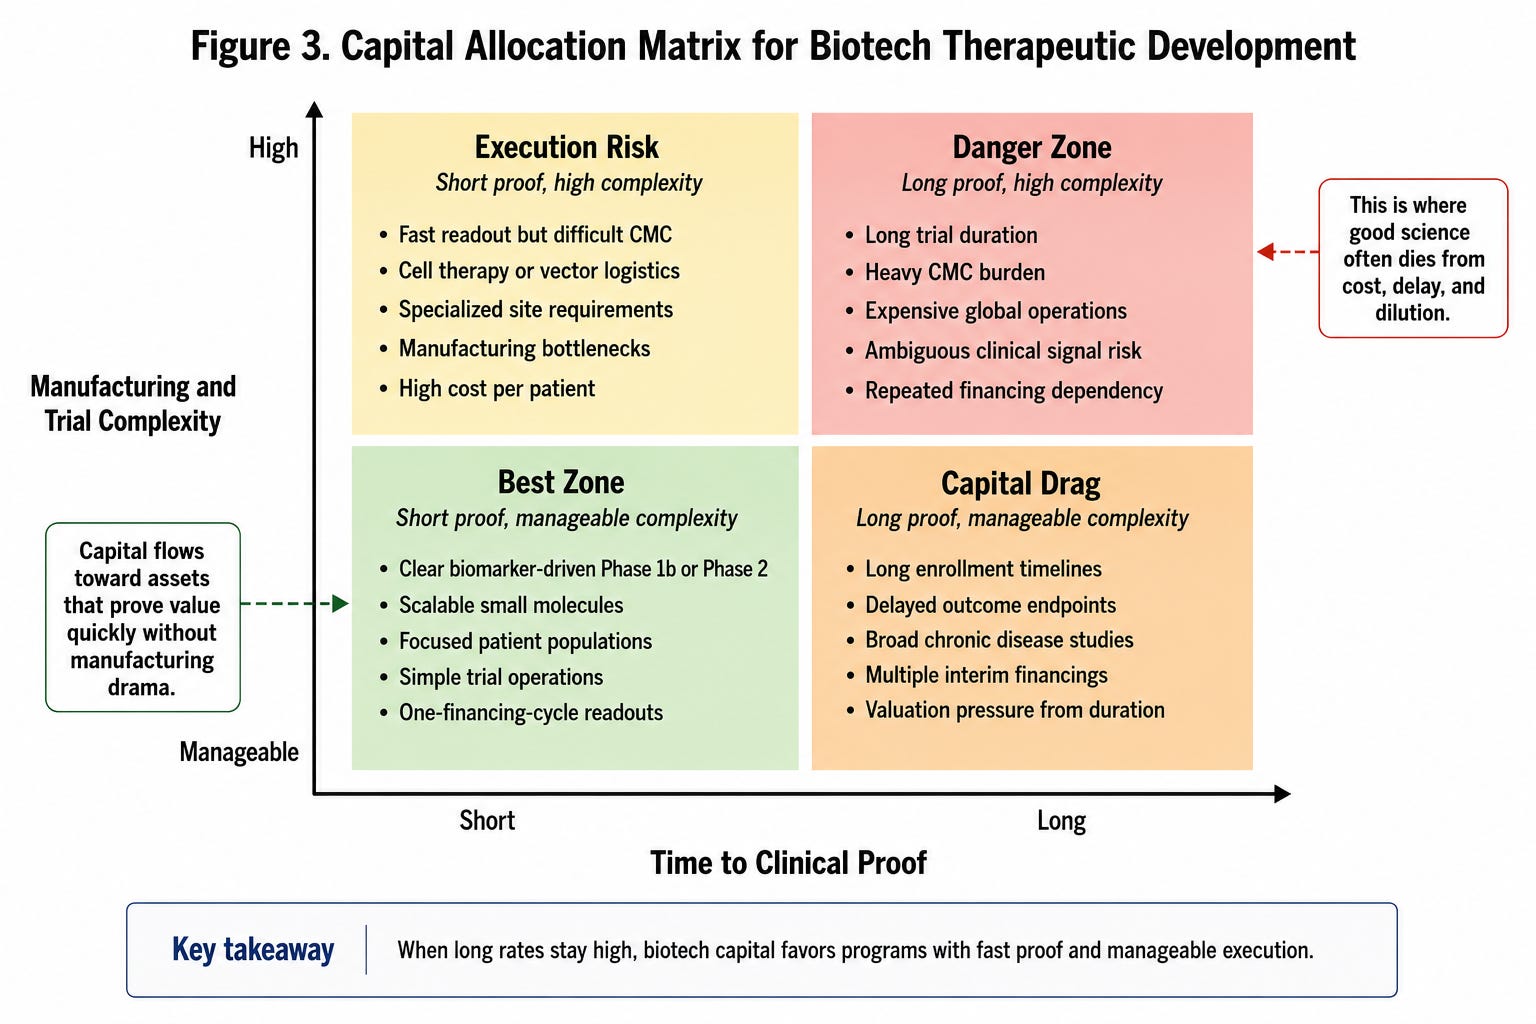
The CMC line item is becoming a macro variable
Investors usually treat CMC as a technical diligence item. That is too narrow. Energy shocks, tariffs, shipping friction, and reagent inflation all flow through CMC. Small companies feel it first because they lack purchasing leverage and redundancy. KPMG noted that smaller research firms and medical product providers are seeing rising costs for imported reagents, consumables, and equipment while broader tariff effects remain uneven across life sciences. That is not a footnote. That is a financing risk.
The implication for therapeutic development is uncomfortable. A modality can be scientifically elegant and financially wrong for the moment. Cell therapy, complex biologics, viral vectors, and programs requiring specialized global supply chains face a higher bar when money is expensive and input costs are unstable. This does not mean the science is bad. It means the capital path has less room for mistakes. A small molecule with rapid proof of mechanism and scalable manufacturing can look boring in the lab and superior in the market.
This is where people underwrite the wrong thing. They compare efficacy curves and forget the manufacturing curve. They ask whether the drug works and ignore whether the company can afford to prove it works. In a tighter macro tape, the second question can kill you before the first question gets answered.
Clinical trials need to look more like stress tests
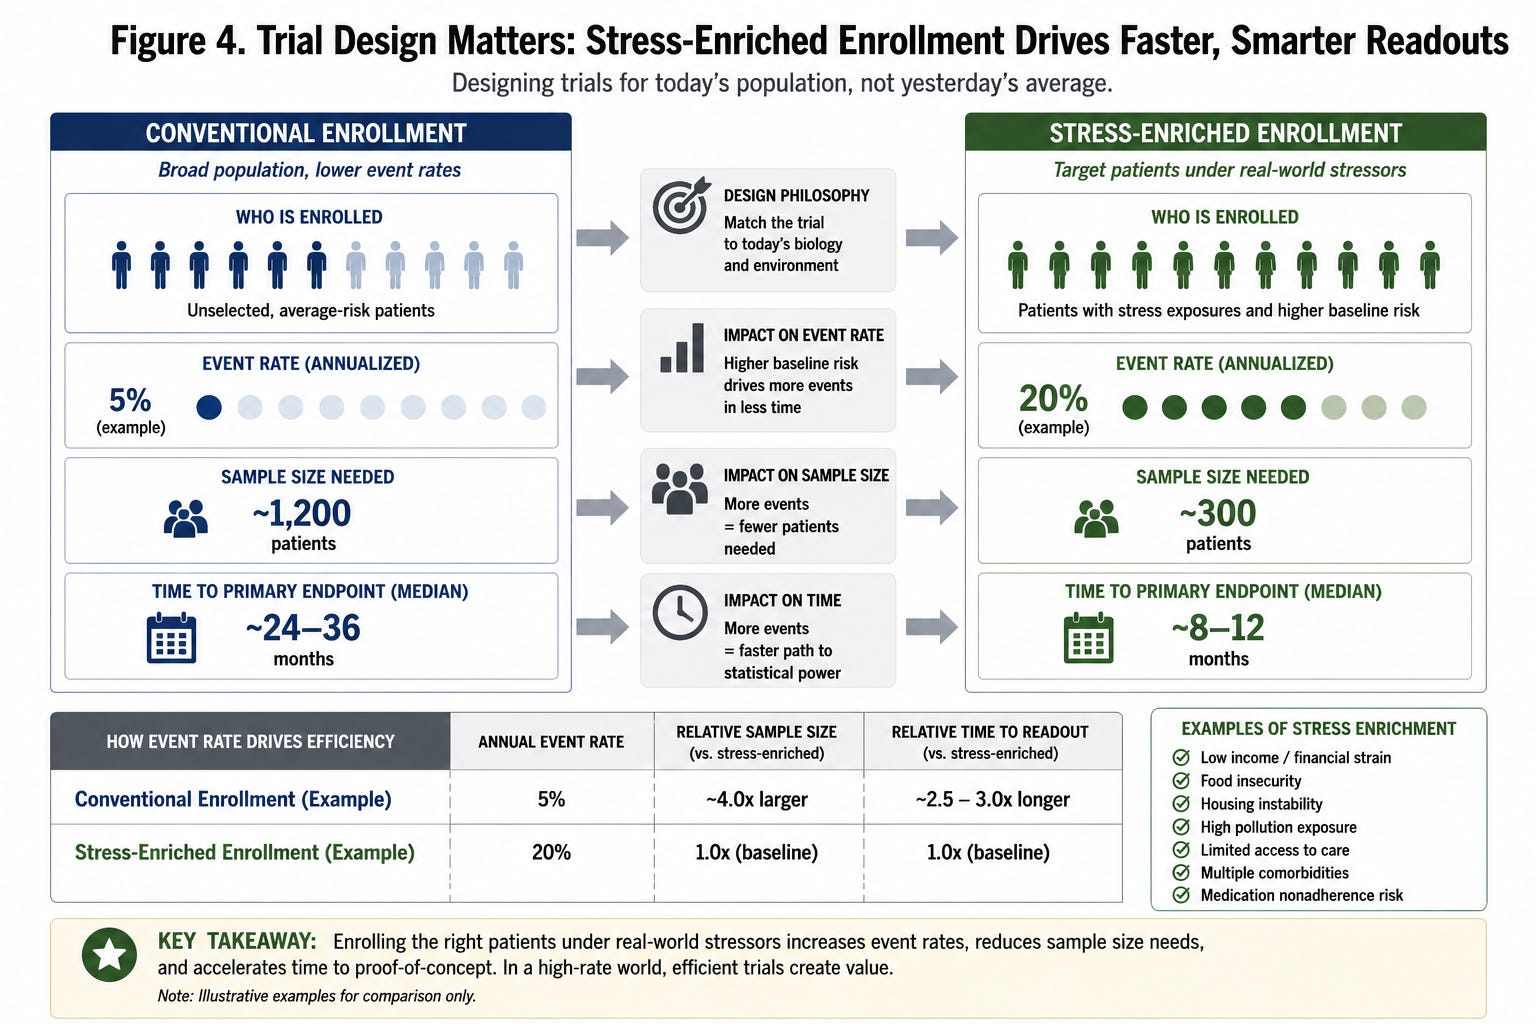
Traditional trial design assumes noise is the enemy. For resilience medicine, some noise is the point. If a drug is supposed to prevent decompensation under environmental or economic stress, the trial should capture stress rather than wash it out. That means enrolling patients during high risk seasons, using geography as an enrichment tool, and linking trial events to external data like temperature, air quality, infection waves, and medication access disruption.
This approach is not just scientifically interesting. It is capital efficient. Higher baseline event rates reduce sample size and shorten timelines. A COPD prevention study enriched around poor air quality periods can reach events faster than a broad all comers trial. A cardio renal trial focused on heat vulnerable patients can test a sharper hypothesis than a generic chronic disease design. A maternal health program in regions with energy instability can show real world utility faster than a polished trial in low risk academic centers.
There is a risk. Enrichment can overfit. A drug that works only in a narrow stress context may struggle commercially unless the label and payer story line up. But that is a better problem than running a giant neutral trial because you ignored the biology of stress. The future of translational development will use external stressors as part of the model, not just as background noise.
The payer angle is better than investors think
Payers do not like paying for biology. They pay when biology turns into fewer claims. That makes resilience therapeutics more interesting than they first appear. A drug that reduces hospitalizations during heat waves, pollution spikes, or infection seasons has a budget story that a biomarker only asset does not. The payer does not need to care about your pathway slide. The payer needs to see fewer admissions, fewer ICU days, fewer readmissions, and fewer expensive rescue interventions.
This creates a development opening for companies willing to design trials around economic endpoints early. Not as decorative secondary endpoints. As part of the core product thesis. Time to hospitalization, rescue medication use, steroid bursts, dialysis initiation, emergency department visits, and home oxygen escalation are not just clinical details. They are reimbursement language. If you wait until Phase 3 to add them, you are late.
The skeptical view still matters. Payers resist new chronic drugs, especially when the target population is broad. Resilience medicine works best when the population is narrow enough to price and identify. Frail heart failure patients. Severe COPD patients. CKD patients with heat vulnerability. Infants during RSV season. Immunocompromised patients during viral waves. The broader the claim, the weaker the payer story. The narrower the use case, the cleaner the economics.
AI will not save every biotech, but it helps here
AI is absorbing market capital right now. That hurts biotech attention. But the same AI infrastructure can help therapeutic developers if they use it for the right job. Not magic target discovery. Not another platform deck. The useful job is prediction. Which patient is about to decompensate. Which site will enroll during the relevant stress window. Which external variable drives event risk. Which biomarker actually moves before the hospitalization happens.
This is one of the few places where AI and biotech fit without sounding fake. Resilience therapeutics need dynamic risk stratification. Static inclusion criteria miss too much. A model that combines weather, air quality, claims history, wearable data, lab trends, and medication adherence can create trial populations with higher event rates. Higher event rates mean faster proof. Faster proof means lower financing risk.
The catch is that regulators and clinicians will not accept a black box just because it improves enrollment. Companies need simple, auditable tools. Think risk scores that a site investigator understands. Think predefined enrichment rules. Think external data sources that can be validated. The AI company that promises omniscience loses trust. The biotech that uses AI to make a trial cheaper and more reproducible gets funded.
Licensing will favor assets that solve timing
J.P. Morgan reported that biopharma licensing reached $77.3 billion in announced value in Q1 2026 while upfront cash represented only 6 percent of total deal value. That number matters. It tells you the market is open, but the money is structured. Pharma wants options. It wants access without taking full balance sheet risk upfront.
Energy shocks and high rates make that behavior more rational. Pharma does not need to buy every public biotech with a decent story. It can license assets after early proof, push risk into milestones, and keep its powder dry. That means therapeutic developers should build toward licenseable proof packages, not just public market hype cycles. A clean Phase 2 that shows event reduction in a high risk stress enriched population is licenseable. A platform with five preclinical indications and no human tissue validation is not.
This also changes China strategy. If Chinese biotechs can deliver credible assets faster and cheaper, U.S. companies need a sharper reason to exist. The answer cannot be patriotism or brand name science. It has to be translational quality, regulatory strategy, trial execution, and payer fit. In a world where licensing eats M&A, the best biotech companies design the asset package that pharma can underwrite quickly.
The hidden opportunity is not another platform
The opportunity is a new class of therapeutic companies built around stress biology, fast translation, and capital efficient endpoints. These companies will not look like 2021 platform stories. They will look narrower. That is good. A company focused on preventing heat associated kidney injury in CKD patients sounds smaller than a universal inflammation platform. It is also easier to test, easier to explain, and easier to partner if the data are real.
Specific ideas worth watching. First, cardio renal drugs developed around heat and dehydration vulnerability, with endpoints tied to AKI, heart failure admissions, and biomarker deterioration. Second, respiratory drugs or biologics tested around pollution linked exacerbations, not generic mild to moderate populations. Third, infectious disease products that protect frail or immunocompromised patients during seasonal surges, with hospital avoidance as the core economic claim. Fourth, maternal and neonatal interventions in regions where heat and energy instability worsen outcomes. Each idea has problems. That is the point. Good biotech ideas should have edges you can diligence.
The best version of this field will borrow from disaster medicine without becoming disaster medicine. It will use environmental stress to reveal biology faster. It will use claims data to prove value. It will use biomarkers to avoid waiting years for outcomes when shorter signals work. That combination is rare. It is also exactly the kind of translational setup investors should want when long rates make time expensive.
What bears will say
The bear case is strong. Energy shocks are episodic. Oil prices fall. The market forgets. A biotech company cannot build a durable therapeutic thesis around the price of Brent crude. That criticism is fair if the company only has a macro story. It is not fair if the macro story identifies a repeatable clinical stressor with measurable biology and reimbursable outcomes.
Another bear point is that climate and energy stress add heterogeneity. Trials already struggle with noise. Adding real world instability can make data harder to interpret. True. That is why the field needs sharp enrichment, predefined external variables, and endpoints that do not require heroic interpretation. If every subgroup analysis becomes the story, the program failed. If the trial prospectively tests a stress linked hypothesis and wins, the data become more useful than a broad average effect.
The biggest bear point is commercial. Payers can agree that hospital avoidance matters and still refuse broad coverage. This pushes the field toward targeted labels first. Severe patients. High risk windows. Clear utilization savings. Start where the payer pain is obvious. Expand later only if the data earn it.
What this means for biotech investors now
For public biotech, this framework gives you a better screen. Ask whether the company’s lead program becomes more attractive when time is expensive. If the answer is no, be careful. A long trial, vague endpoint, high CMC burden, and weak financing path does not become interesting because the stock is down 80 percent. It often deserves to be down.
Look for companies that can produce decisive human data without needing a perfect macro tape. Balance sheet matters. Trial design matters more than investors admit. Manufacturing simplicity matters more than platform breadth. A biotech that can show a real clinical or biomarker signal in a high event population within one financing cycle deserves attention. A company that needs the window to stay open for two more years is asking you to underwrite Jerome Powell, oil shipping lanes, and clinical biology at the same time.
The broader point is that macro is no longer separate from therapeutic development. It decides which programs get funded, which trials get designed, which endpoints matter, and which companies survive long enough to be right. Energy shocks and long rates do not just pressure biotech valuations. They force a better version of biotech. Less theater. Fewer platform slides. More proof.
The future shape of translational development
The next wave of translational winners will treat the outside world as part of the disease model. That means stress enriched cohorts, external data linked endpoints, tighter patient selection, and trials built to answer payer relevant questions early. The companies that do this well will look less like discovery engines and more like clinical intelligence businesses wrapped around a drug.
This will also change how pharma buys. Pharma will not just ask whether a target is novel. It will ask whether the asset solves a timing problem. Can it produce proof fast. Can it plug into an existing commercial channel. Can it defend reimbursement. Can it avoid a manufacturing headache. The drug with slightly less theoretical upside but a cleaner answer to those questions wins more often than investors expect.
That is the part people are missing. Energy volatility looks like a macro nuisance. Long rates look like a valuation input. Together they are shaping therapeutic taste. They reward drugs that protect vulnerable patients during stress and punish companies that treat time as free. The opportunity is not to predict oil. The opportunity is to build and own the biology that becomes more valuable when the world gets less stable.
CONCLUSION
Today the biotech lesson is simple. The discount rate is no longer a spreadsheet input you hide in the model. It is a development constraint. Companies that need cheap time, forgiving investors, and perfect capital markets will keep struggling, even when the science looks fine. The more interesting opportunity sits in programs that can prove human biology quickly, reduce real clinical events, and protect vulnerable patients when the outside world gets less stable. That is where macro stops being background noise and starts becoming a therapeutic thesis.
We are now publishing 7x per week according to the following cadence:
Mondays: Stocks
Tuesdays: Biotech
Wednesdays: Podcast
Thursdays: Markets
Fridays: News
Saturdays: Podcast
Sundays: Strategy
SUBSCRIBE TO PODCAST HERE:
Sundays and Mondays are under the paid umbrella, everything else is FREE. It is $11.99/month and we encourage you to support our efforts. It keeps us motivated to keep producing the hybrid science and business biotech focused content you will not find anywhere else all in the same place.
As a reminder, if looking to go deeper into the topics we cover check out our website BowTiedBiotech.com, or DM us on twitter, or email us: bowtiedbiotech@gmail.com
ABOUT BOWTIEDBIOTECH
As a reminder, the purpose of the BowTiedBiotech substack is two-fold. Primarily, we aim to provide our scientist audience the tools to build a biotech company and ultimately translate their ideas into medicines for patients. Secondarily, biotech investors may find this substack useful as we will be providing weekly market updates of the public AND private markets as well as heavily leveraging current financing events as teaching examples.
DISCLAIMER
None of this is to be deemed legal or financial advice of any kind. All updates are sourced from publicly available disclosures. Insights are *opinions* written by an anonymous cartoon/scientist/investor.
The discount-rate-as-clinical-endpoint framing is the kind of cross-domain thinking most biotech analysis doesn't attempt. Most people in your lane either do pure science or pure finance and never bridge them. The argument that the time-value-of-money assumptions in NPV models literally shape which drugs get developed is one I want to sit with. Would love a follow-up applying this to the GLP-1 cohort specifically.