

Hello Avatar! Welcome to another week of biotech analysis. Today’s commentary, as always on Thursday, focuses on the general market update. This week confirmed the playbook. Biotech can rally and capital can return quickly, but funding is flowing to companies with clean catalysts and tight execution. Secondaries continue to dominate the financing landscape, while IPO activity remains scarce. Investors are rewarding near-term proof and punishing duration risk. In this environment, cost of capital shapes trial design, and clock discipline matters as much as mechanism.
We are now publishing 7x per week according to the following cadence:
Mondays: Stocks
Tuesdays: Biotech
Wednesdays: Podcast
Thursdays: Markets
Fridays: News
Saturdays: Podcast
Sundays: Strategy
We are also publishing unique content on X - be sure to follow up if you are not already @BowTiedBiotech. And to check-out the archive of our work on X you can find it on our website at: BowtiedBiotech.subtack.com/x-articles.
SUBSCRIBE TO PODCAST HERE:
Please help spread the work by subscribing and hitting the share button if you are enjoying content!
Lots to cover this week, let's get started!
BIOTECH PUBLIC MARKET UPDATE
For the week, the public indexes were UP, with the S&P +0.5% & DOW moving +0.7%. For the year the public indexed are UP the S&P is up +7.7% and DOW is up +5.5%. The XBI (the biotech index) comes in UP +1.77% for the week and is up +9.9% for the year.

Macro Update
AI's Power Hunger Is Becoming A Biotech Problem
Most investors view the AI infrastructure buildout as a technology story. Nvidia sells chips. Hyperscalers build datacenters. Utilities scramble to keep up. Biotech appears completely disconnected from this trend.
Look closer. Modern biotech increasingly runs on the same infrastructure AI is consuming. Cell therapy manufacturing, biologics production, sequencing centers, high-performance computing clusters, cryogenic storage facilities, and AI-enabled drug discovery platforms all require significant amounts of power. The assumption has always been that electricity would remain abundant and relatively cheap. That assumption is starting to break down.
The scale of the AI buildout is difficult to appreciate. Utilities across major markets are receiving power requests that would have seemed absurd only a few years ago. New datacenters are demanding hundreds of megawatts at a time. In some regions, utility interconnection queues stretch years into the future. Every megawatt directed toward AI infrastructure is a megawatt unavailable for other industrial users. The result is rising power costs, longer project timelines, and growing competition for electrical capacity.

This matters for biotech because many of the industry’s most promising areas are also among its most power-intensive. Cell therapy manufacturing facilities require highly controlled environments operating around the clock. Advanced biologics manufacturing relies on increasingly complex production infrastructure. AI drug discovery companies are now competing for the same computational resources as technology firms. Investors spend enormous amounts of time debating clinical endpoints, regulatory outcomes, and competitive landscapes. Few consider that one of the next bottlenecks for biotech scale-up may simply be access to affordable power.
The market still views energy constraints as an AI problem. That is likely a mistake. Over the next decade, electricity becomes a strategic input for biotechnology in the same way semiconductor capacity became a strategic input for artificial intelligence. The companies best positioned to scale may not be the ones with the best science. They may be the ones that secure infrastructure before everyone else realizes it has become scarce.
Introduction
This week we’re stepping back from individual clinical trials and asking a bigger question. What happens when the factory disappears?
For decades, cell therapy has been defined by complexity. Collect cells. Ship them. Engineer them. Expand them. Ship them back. The process works, but it was never designed to scale. A new generation of companies is attempting something far more ambitious. Instead of manufacturing cell therapies in specialized facilities, they want to manufacture them directly inside the patient. If successful, in vivo CAR-T has the potential to reshape not only oncology but the broader future of immune engineering.
We’ll also take a brief look at a seemingly unrelated trend unfolding outside biotech. The race to build AI infrastructure is consuming enormous amounts of power, creating a new class of bottlenecks that few investors are paying attention to. As biotechnology becomes increasingly dependent on advanced manufacturing, computation, and data-intensive research, access to energy is becoming a strategic resource. The next constraint on innovation may not come from biology or regulation. It may come from the electrical grid.
As always, the goal is to identify where the consensus narrative breaks down and where the next opportunity is forming before the market fully appreciates it.
Why in vivo CAR-T is the next real platform fight
CAR-T has always had a manufacturing problem pretending to be a biology problem. We pull T cells out of a patient, ship them, engineer them, expand them, test them, freeze them, ship them back, condition the patient, then reinfuse a living drug weeks later. It works. It also looks insane when you explain it to anyone outside cell therapy.
In vivo CAR-T says the quiet part out loud. Stop manufacturing the cell therapy in a clean room. Manufacture it inside the patient. One IV dose. The vector finds T cells. The T cells express a CAR. The body becomes the bioreactor.
That is why Lilly paid up to $7 billion for Kelonia in April 2026, including $3.25 billion upfront, and why AbbVie bought Capstan for $2.1 billion in 2025. These are not normal early-stage cell therapy deals. These are platform land grabs. Lilly is buying oncology optionality. AbbVie is buying autoimmune optionality. Kite bought Interius for $350 million because the incumbent CAR-T players cannot ignore a technology that attacks their own cost structure.
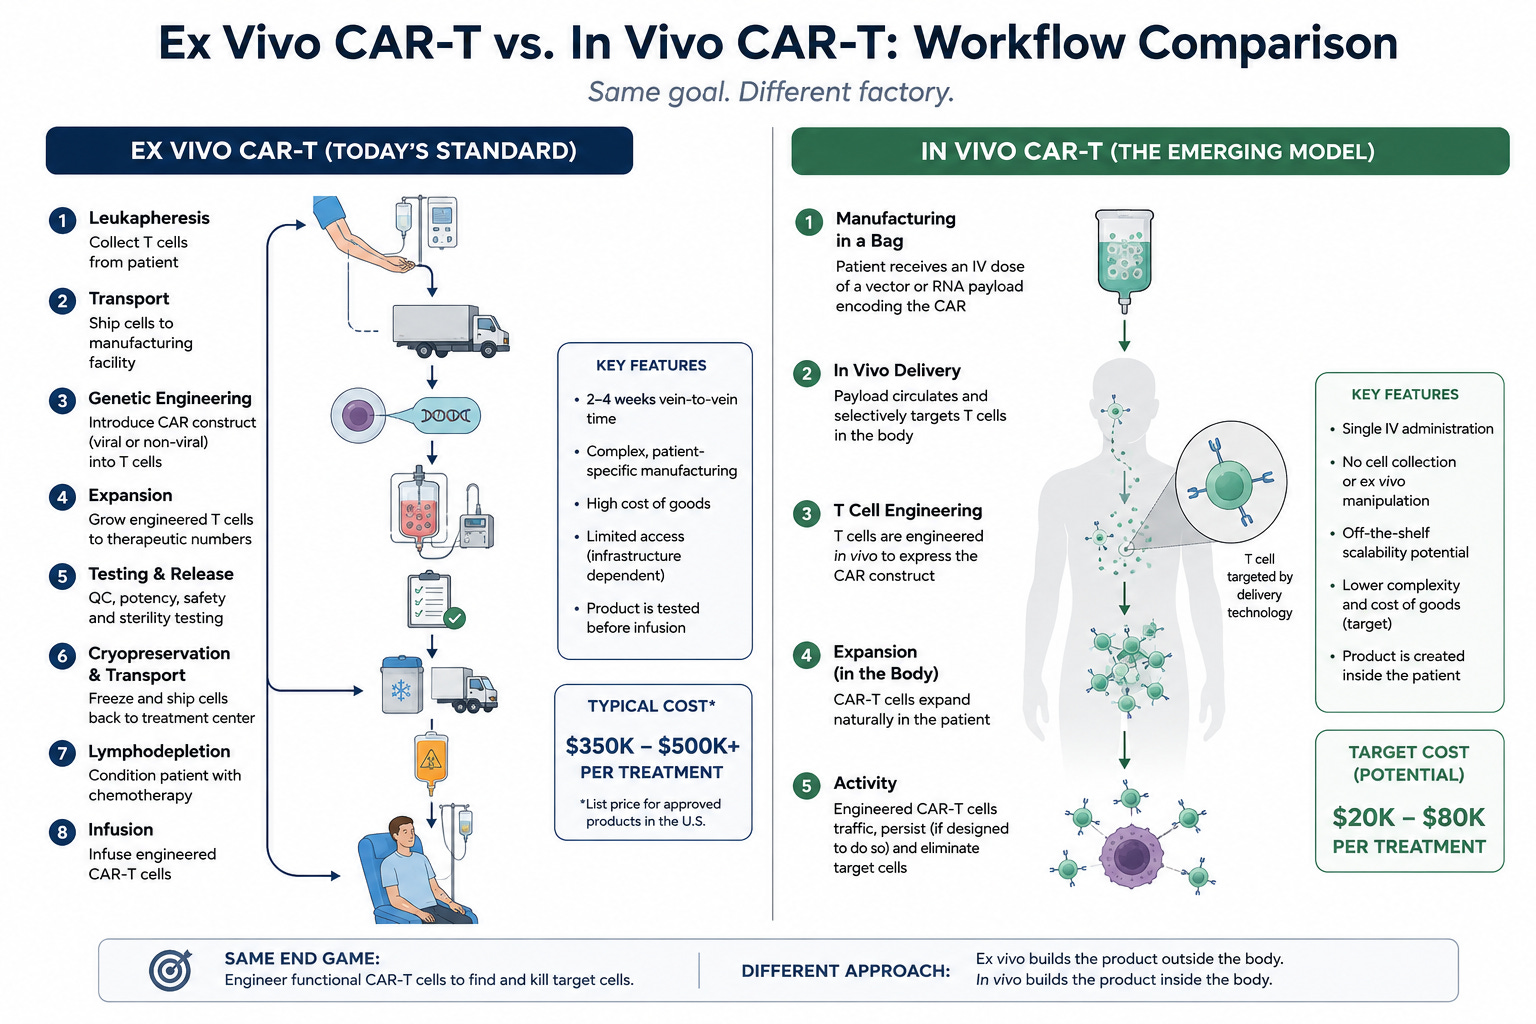
The bull case is obvious. The bear case is better.
The bull case says in vivo CAR-T removes leukapheresis, bespoke manufacturing, vein-to-vein delays, and maybe lymphodepletion. That changes access. It changes gross margins. It lets CAR-T move from late-line blood cancer into autoimmune disease, community oncology, and eventually repeatable immune reset medicine.
The bear case says you are injecting a genetic payload into a sick person and hoping it finds the right immune cells, at the right dose, for the right duration, without creating a runaway immune event. That is not a small ask. Ex vivo CAR-T looks clunky because every variable gets controlled outside the body. In vivo CAR-T looks elegant because many of those variables disappear from view. They do not disappear from biology.
The core question is not whether in vivo CAR-T can make CAR-positive T cells. It can. The better question is whether it can make the right number of useful CAR-T cells inside real patients with bad immune systems. Cancer patients have exhausted T cells. Autoimmune patients often have chronic inflammation and prior immunosuppression. The preclinical monkey does not tell you how a fifth-line myeloma patient responds.
The field is already splitting into multiple technology stacks
One of the biggest mistakes investors make is treating in vivo CAR-T as a single category. It isn’t.
The term describes an outcome, not a technology. Every company wants to engineer immune cells inside the patient. The methods differ dramatically. Those differences will determine where each platform wins and where it fails.
Some companies use targeted lipid nanoparticles carrying mRNA. Others use engineered viral vectors. A third group is pursuing polymeric and other non-viral delivery systems. Each architecture makes different tradeoffs around persistence, safety, manufacturability, and redosing.
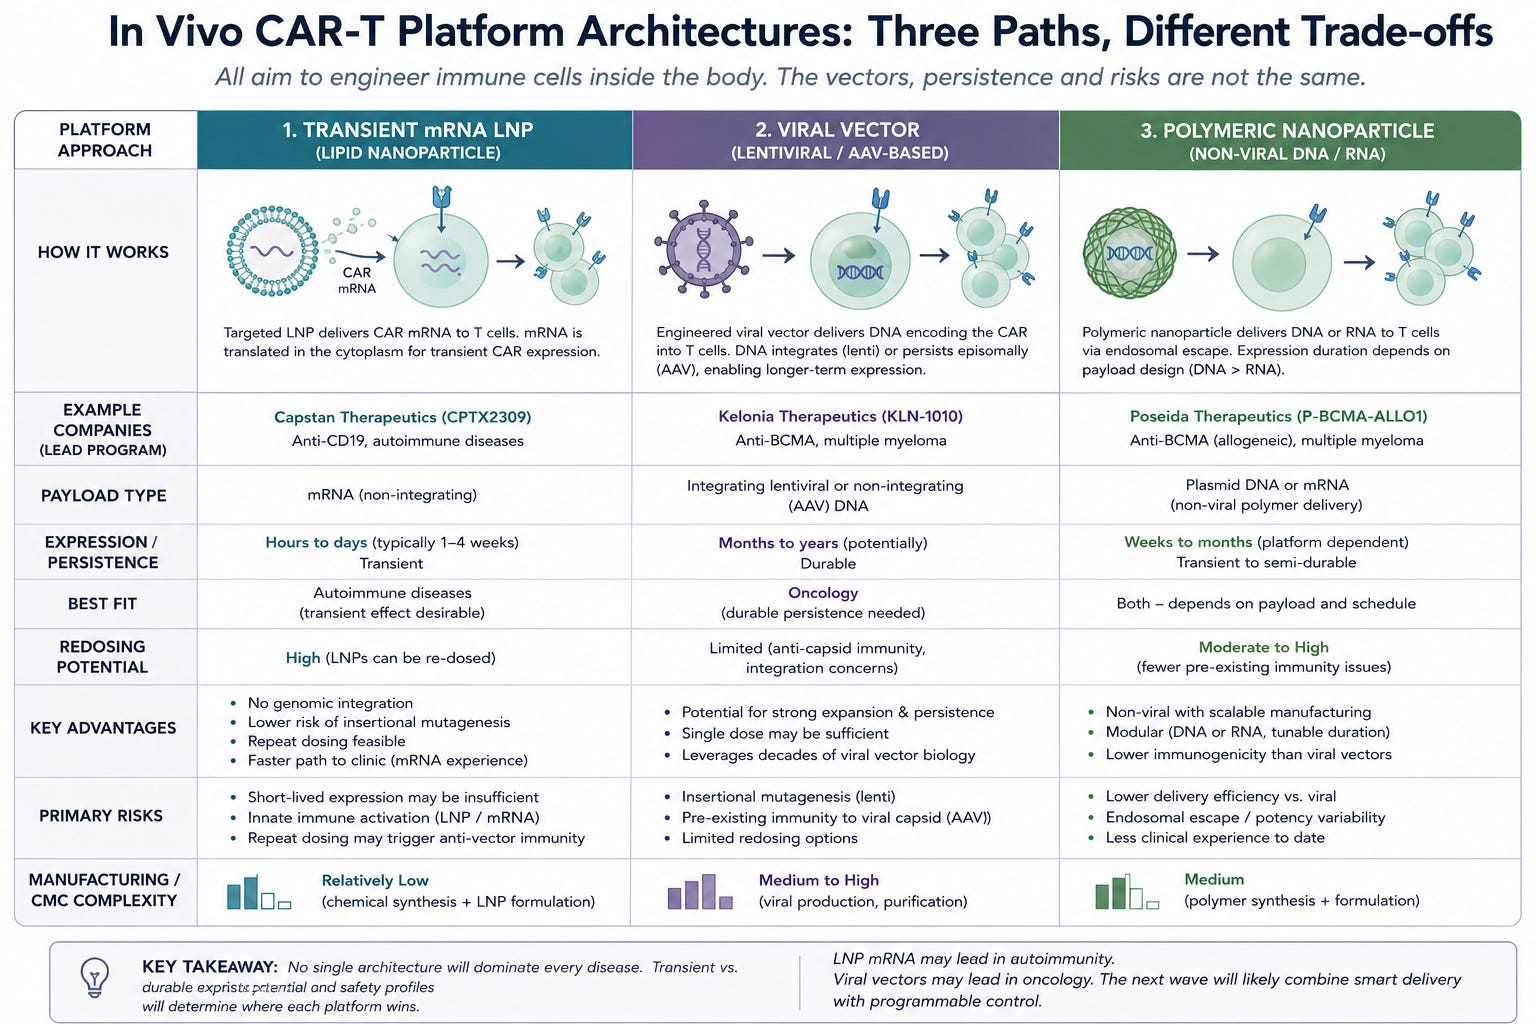
The split is already becoming visible.
mRNA platforms such as Capstan are optimized for transient immune programming. That makes them attractive in autoimmune disease, where physicians want a deep reset without permanent immune modification.
Viral platforms such as Kelonia are pursuing durable expression and sustained activity. That profile fits oncology, where persistence often drives efficacy.
Polymeric and other non-viral systems sit somewhere in between. They receive less attention today, but they may ultimately offer the best balance between efficacy, safety, and scalability.
Most investors focus on the payload. They ask whether a company targets CD19 or BCMA. The more important question is whether the delivery system can reliably generate a therapeutic response across diverse patients. Antigens change. Delivery platforms endure.
That is why AbbVie bought Capstan and Lilly bought Kelonia. Neither company was buying a single asset. They were buying competing visions of how immune cells will be programmed inside the body over the next decade.
The market still talks about in vivo CAR-T as if one platform will dominate every indication. The data suggest the opposite. Oncology and autoimmune disease have different requirements. The eventual winners may emerge from entirely different technology stacks.
The hidden theme is control
Most people talk about access and cost. That is fine. It is also the obvious take.
The real bottleneck is control.
Ex vivo CAR-T gives you control over cell selection, transduction efficiency, expansion, release testing, dose, and product identity. In vivo CAR-T trades that control for speed. You no longer dose cells. You dose instructions. That changes the regulatory problem and the clinical problem.
A 70 kg patient with robust circulating T cells does not equal a 70 kg patient with lymphopenia, recent bispecific exposure, exhausted marrow, and steroid use. Same vector dose. Different cellular factory. Different product. The patient is not just receiving the drug. The patient is part of the manufacturing process.
That is the key investor insight. In vivo CAR-T will not be valued only by target antigen. It will be valued by how well the platform normalizes patient-to-patient variability.
Why autoimmune disease is the cleaner first market
Autoimmune disease is where this story gets interesting.
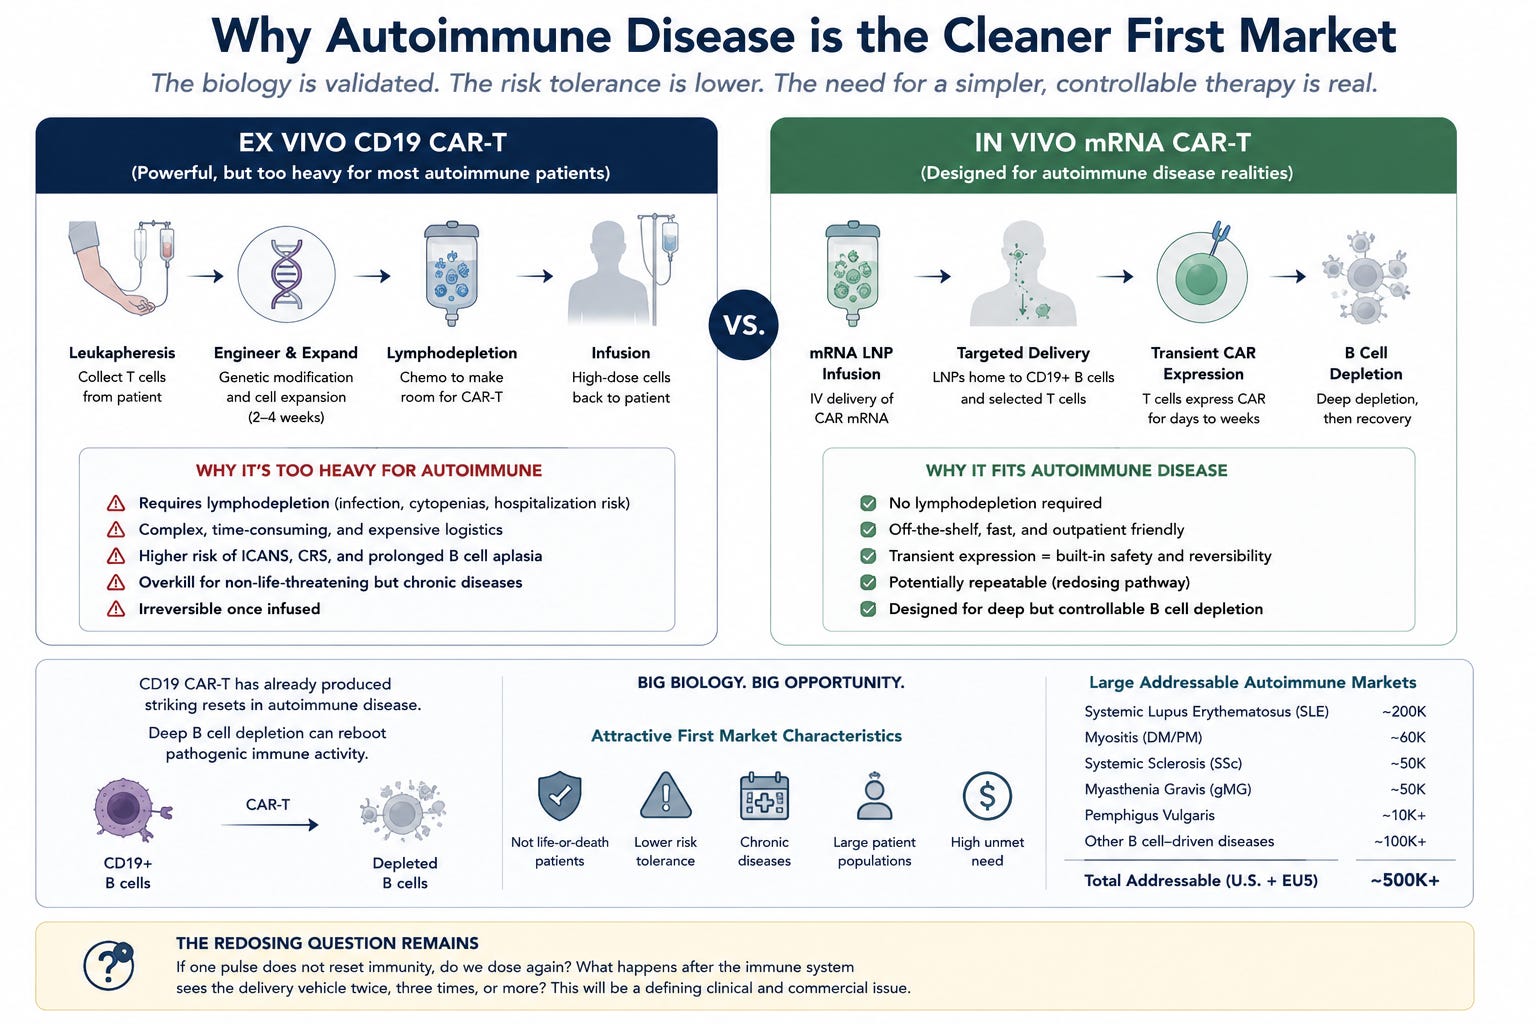
CD19 CAR-T has produced striking resets in autoimmune disease using ex vivo products. The biology is not subtle. Deplete pathogenic B cells hard enough and some patients look like their immune system reboots. That opens lupus, myositis, systemic sclerosis, myasthenia gravis, pemphigus, and other B cell driven diseases.
But ex vivo CAR-T is too heavy for most autoimmune markets. Patients are not terminal oncology patients. They care about infertility risk, infection risk, ICU risk, and long-term safety. Physicians will not casually send stable autoimmune patients through lymphodepletion and bespoke cell therapy logistics.
That is why Capstan mattered. Transient CAR expression solves a real autoimmune problem. You want a hammer, but not a permanent hammer. You want B cell depletion deeper than rituximab, with less infrastructure than ex vivo CAR-T. mRNA delivery gives you that design logic. It also creates a redosing question. If one pulse does not reset immunity, do you dose again, and what happens after the immune system sees the delivery vehicle twice?
Oncology is harder than the press release says
Oncology investors love in vivo CAR-T because it sounds like the natural successor to autologous CAR-T. That view skips over ugly biology.
Blood cancers grow while patients wait. So speed helps. But late-line cancer patients also have damaged immune systems. Their T cells are often exhausted, numerically weak, or recently hit by therapies that alter the same compartments you need for in vivo engineering. You can inject a perfect vector into a poor T cell pool and get a mediocre living drug.
Kelonia’s lead KLN-1010 targets BCMA in relapsed or refractory multiple myeloma and is already in Phase 1. That target choice is smart and dangerous. Smart because BCMA is validated. Dangerous because BCMA is crowded, expectations are high, and comparators exist. Investors will not give much credit for “we made CAR-T cells in vivo” if response depth, durability, CRS, ICANS, and infection burden look ordinary.
The first oncology wins probably come where speed beats perfection. A product that treats faster, reaches more patients, and avoids manufacturing failure can win even with somewhat weaker efficacy. But it cannot be weak. This field dies quickly if in vivo CAR-T becomes “convenient but less potent.”
The most interesting idea is not CAR-T
Here is the part people underweight.
In vivo CAR-T is a gateway drug for in vivo immune programming.
Once you can target T cells in the body, the CAR is just the first payload. You can deliver TCRs, cytokine circuits, exhaustion resistance modules, transient gene editors, tolerogenic programs, or suicide switches. You can also target NK cells, Tregs, monocytes, or tissue resident immune cells.
That means the platform companies are not just building cheaper CAR-T. They are building immune cell routers. The company that learns how to deliver genetic instructions to selected immune cells in vivo owns a much broader design space than CD19 or BCMA.
This is why the delivery layer matters more than the first asset. A mediocre first CAR can still prove targeting, biodistribution, expression kinetics, and redosing. A clean delivery dataset is worth more than one antigen program. Watch the biodistribution tables. Watch off-target transduction. Watch whether they show single-cell data. That is where the platform truth hides.
The short thesis
The short thesis is simple.
These companies are being priced as if delivery specificity is solved. It is not solved. It is improving.
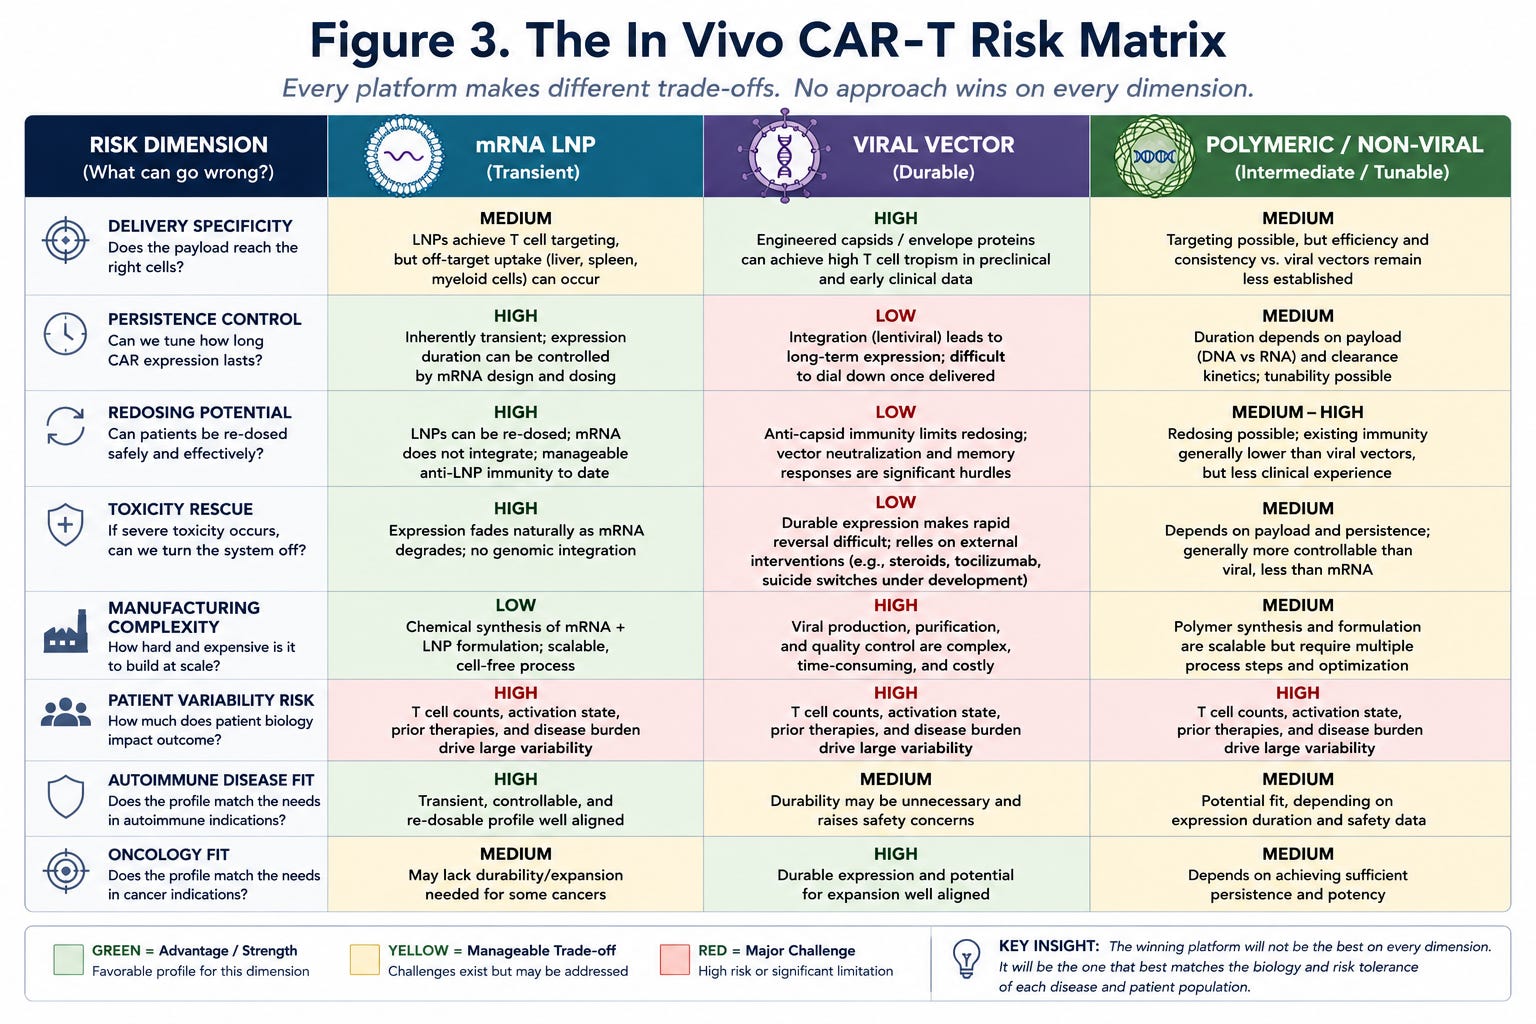
The body does not like nanoparticles floating around. The liver catches things. The spleen catches things. Myeloid cells eat things. Antibodies bind things. Complement activates. Viral vectors bring insertion and immunogenicity questions. LNPs bring repeat dosing and innate immune activation questions. Polymer systems bring their own tolerability and CMC questions.
The FDA will ask uncomfortable questions. What exact cells were modified? Where else did the payload go? How long did expression last? What happens if a patient has low T cell counts? Can you rescue severe toxicity if the factory is inside the patient? What is the release test when the final product forms after dosing?
That last question is brutal. For ex vivo CAR-T, the product gets tested before infusion. For in vivo CAR-T, the final pharmacologic product emerges inside the patient. Regulators will not ignore that.
What nobody is saying out loud
In vivo CAR-T also changes power inside hospitals.
Today, major academic centers control much of cell therapy because they have the infrastructure. They have leukapheresis workflows, cell therapy units, ICU familiarity, and trained teams. If in vivo CAR-T becomes a true IV medicine, the center of gravity moves.
Community oncology wants this. Rheumatologists want this even more, assuming safety improves. Big Pharma wants it most. A scalable IV product fits their commercial machine. Bespoke cell therapy does not.
That is the second-order trade. In vivo CAR-T threatens not only autologous manufacturing. It threatens the institutional moat around CAR-T delivery. The winners become companies with delivery IP, scalable CMC, and disease-area sales infrastructure. The losers are not only weak cell therapy biotechs. The losers include service layers built around complexity.
The future probably looks split
Oncology and autoimmune disease will not converge into one product model.
Oncology needs potency. It needs expansion. It needs persistence. It probably accepts more risk. Viral in vivo platforms make sense there, especially if they show clean T cell selectivity and strong expansion in patients.
Autoimmune disease needs controllability. It needs repeatability. It needs safety in patients who have treatment options. Transient mRNA platforms make more sense there. The winning autoimmune product does not need to look like axi-cel. It needs to look like a deep immune reset that a rheumatologist can defend.
That split matters. Do not evaluate every in vivo CAR-T platform with the same lens. A transient CD19 mRNA product can look underpowered for lymphoma and still look perfect for lupus. A durable lentiviral BCMA product can look too risky for broad autoimmune use and still make sense in myeloma.
What to watch next
Watch these four things.
Target cell purity. If a company cannot show convincing T cell selective delivery in primates and humans, discount the platform.
Expression kinetics. Transient is not bad. Permanent is not good. The right answer depends on disease.
Patient variability. The key clinical dataset is not the average CAR-positive T cell percentage. It is the spread across patients.
Redosing. This is the sleeper issue. If the platform cannot redose cleanly, chronic and autoimmune markets shrink.
The investment setup
The field has entered the expensive proof stage.
Lilly, AbbVie, and Kite have already told you the strategic value. Lilly’s Kelonia deal is the loudest signal because the upfront alone was $3.25 billion. AbbVie’s Capstan deal confirms autoimmune demand. Kite’s Interius deal confirms incumbents are hedging their own model.
But big checks do not validate biology. They validate fear of missing the platform. Pharma buys these assets because the upside is existential. If in vivo immune engineering works, ex vivo cell therapy becomes the expensive first draft.
The best near-term public market angle is not “buy every in vivo CAR-T story.” That is how you get wrecked. The better angle is to map who owns delivery, who owns validated antigen biology, who owns autoimmune commercial infrastructure, and who owns toxicity management. The value will not distribute evenly.
Final read
In vivo CAR-T is one of the few biotech themes that deserves the hype and the skepticism.
The opportunity is real. A single infusion that programs immune cells inside the body changes cost, access, and disease scope. It turns CAR-T from a hospital-manufactured rescue therapy into a programmable drug class.
The risk is also real. The body is a messy factory. You do not get to QC the final product before it exists. You do not get clean patients. You do not get perfect delivery. You get biology.
That is why this field is compelling. Not because it makes CAR-T cheaper. Because it forces a bigger question.
Can we turn immune cells into programmable therapeutics without touching them outside the body?
If the answer is yes, CAR-T is only the first chapter. If the answer is no, the next few years will be a very expensive reminder that manufacturing complexity sometimes exists for a reason.
CONCLUSION
Today, the most interesting opportunities in biotech are emerging at the intersection of disciplines. The future of cell therapy is increasingly becoming a delivery problem. The future of drug discovery is increasingly becoming a computation problem. And the future of scaling biotechnology may increasingly become an infrastructure problem. Investors who focus only on clinical data risk missing the larger forces shaping the industry. The next generation of winners will not simply have the best biology. They will have the platforms, manufacturing capabilities, and infrastructure needed to translate that biology into products at scale. As always, our goal is to identify those shifts before they become consensus.
We are now publishing 7x per week according to the following cadence:
Mondays: Stocks
Tuesdays: Biotech
Wednesdays: Podcast
Thursdays: Markets
Fridays: News
Saturdays: Podcast
Sundays: Strategy
SUBSCRIBE TO PODCAST HERE:
Sundays and Mondays are under the paid umbrella, everything else is FREE. It is $11.99/month and we encourage you to support our efforts. It keeps us motivated to keep producing the hybrid science and business biotech focused content you will not find anywhere else all in the same place.
As a reminder, if looking to go deeper into the topics we cover check out our website BowTiedBiotech.com, or DM us on twitter, or email us: bowtiedbiotech@gmail.com
ABOUT BOWTIEDBIOTECH
As a reminder, the purpose of the BowTiedBiotech substack is two-fold. Primarily, we aim to provide our scientist audience the tools to build a biotech company and ultimately translate their ideas into medicines for patients. Secondarily, biotech investors may find this substack useful as we will be providing weekly market updates of the public AND private markets as well as heavily leveraging current financing events as teaching examples.
DISCLAIMER
None of this is to be deemed legal or financial advice of any kind. All updates are sourced from publicly available disclosures. Insights are *opinions* written by an anonymous cartoon/scientist/investor.